


| Soo Young Kim | 4 Articles |
Background
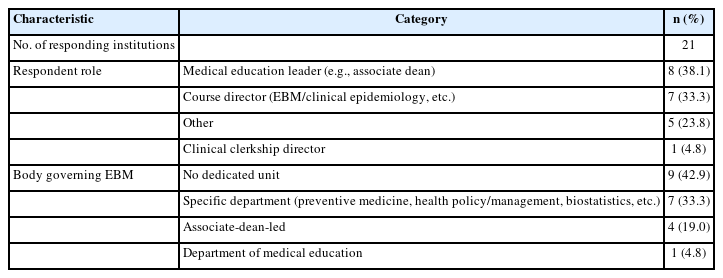
Evidence-based medicine (EBM) is an important element of medical education. However, nationwide data on EBM education in Korean medical schools are limited. This study aimed to describe the organizational structure, content, methods, and assessment of EBM education, together with barriers and support needs, and to explore factors associated with variation across schools. Methods A 26-item questionnaire was administered to EBM education leaders or course directors at 21 Korean medical schools. Data were analyzed descriptively, and differences by structural and exogenous characteristics were explored using cross-tabulation. Results Twenty-one of 40 medical schools responded. All responding institutions offered EBM as a mandatory subject, but 42.9% had no dedicated organizing unit. Coverage of classic EBM steps was high (formulating clinical questions: 95.2%; literature searching: 95.2%; critical appraisal: 76.2%), whereas AI-assisted evidence summarization was included in only 19.0%. Only 19.0% reported systematic theory–clinical integration, and 57.1% left bedside EBM to preceptor discretion. Demand for a standardized curriculum guide (90.5%) and faculty development (76.2%) was high, and 100% were willing to use externally developed materials. Variation in key outcomes was associated with organizational governance but was not explained by exogenous structural characteristics such as class size, clinical infrastructure, establishment type, or region. Conclusions EBM education in Korean medical schools is universally mandatory but uneven in organization, theory–clinical integration, faculty capacity, assessment, and AI integration. These differences appeared to reflect governance more than resource size, suggesting that society-level support should include organizational models alongside standardized curricula, assessment tools, and faculty development.
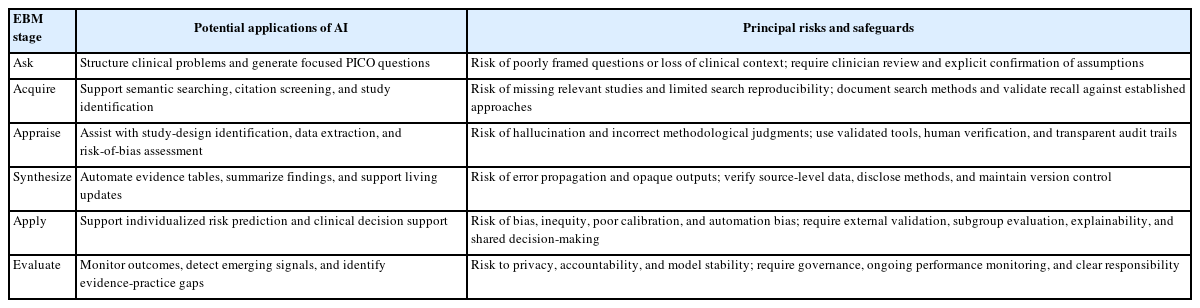
Evidence-based medicine (EBM) has transformed clinical decision-making by integrating the best available research evidence with clinical expertise and patients’ values and preferences. Over the past three decades, EBM has evolved from the critical appraisal of individual studies into a broader framework encompassing evidence synthesis, clinical practice guidelines, assessment of evidence certainty, research transparency, and shared decision-making. Despite these advances, contemporary EBM faces important challenges, including the rapidly increasing volume of research, delays in evidence synthesis and implementation, limited applicability of randomized controlled trials to heterogeneous real-world populations, and difficulties in individualizing population-level evidence. Emerging approaches—including real-world evidence, living evidence, learning health systems, precision medicine, and artificial intelligence (AI)—offer opportunities to address these limitations. Together, these approaches may enable a transition from static to continuously updated evidence, from population-average to more personalized evidence, and from a linear evidence pipeline to a learning evidence ecosystem in which clinical practice both uses and generates evidence. AI may further accelerate evidence retrieval, synthesis, updating, and individualized decision support, while introducing challenges related to reliability, bias, transparency, reproducibility, and accountability. Next-generation EBM should therefore be conceptualized not as a replacement for traditional EBM but as its evolution into a digitally connected, continuously learning evidence ecosystem. In the AI era, the foundational principles of EBM—source verification, critical appraisal, uncertainty assessment, integration of patient preferences, and accountable human judgment—will become increasingly important.
Evidence-Based Practice (EBP) is an approach that utilizes the best evidence for patient care, and its importance is growing in various fields to improve patient-centered care. However, the Evidence-Practice Gap (EPG) that occurs in the practical application of EBP remains a significant problem. EPG refers to the gap between research results and actual clinical practice, which can hinder the optimization of patient care and lead to inefficiencies in the healthcare system. This review introduces the concepts of EBP and EPG and examines educational approaches such as Sicilian statements and Core Competencies in Evidence-Based Practice. In addition, we discuss translational research, knowledge transfer, multidisciplinary collaboration, and evidence-based policymaking, which are key efforts to resolve EPG. In addition, we emphasize the importance of setting research directions using the Evidence Gap Map (EGM) along with national strategies to promote the spread of EBP. This paper discusses how strategic approaches and policy efforts to resolve the EPG can contribute to the actual clinical application of EBP, and suggests future research directions.
Citations Citations to this article as recorded by

Background
In the case of clinical practice guideline (CPG), the need for the prospective registration of protocols has been proposed several times. However, the registration of CPG protocols is not yet active. The objective of this study was to summarize the experience of the CPG protocol registration program in Korea. Methods This study was performed in the following order: 1) formation of a methodological expert group; 2) CPG protocol template development; 3) CPG protocol preparation and expert review; 4) exploration of the knowledge and attitude of the guideline developers toward CPG protocol. Results The final version of the CPG protocol templates consists of four parts (planning, development, finalization, and timetable). The protocols for 18 cancers were submitted by 14 medical societies. conflicts of interest (n = 14, 77.8%), guideline development group (GDG; n = 9, 50%), scope of CPG (n = 9, 50%), and key questions (n = 8, 44.4%) were the under-reported areas in the submitted protocols. The GDGs (n = 13, 72.7%) was the most misreported areas of the protocol. CPG developers generally agreed on the advantages of protocol registration but responded that it was difficult to understand the concepts in the protocol and fill them with appropriate content. The areas where CPG developers responded that they felt difficulty were were recommendation grade (n = 9, 75.0%), GDG composition (n = 7, 58.3%), and determining key questions (n = 7, 58.3%). Conclusions The CPG protocol registration program was planned and piloted in Korea, and it could be said that it is feasible. It is necessary to evaluate the developed CPG later and determine whether protocol registration affects the quality of CPG through indices such as transparency and clarity of CPG.
|
|

